
EPISODE · Sep 15, 2026 · 42 MIN
PSYCH 123: Anxiety Disorders - Somatic Therapies
from Clinical Deep Dives · host Dr Manaan Kar Ray
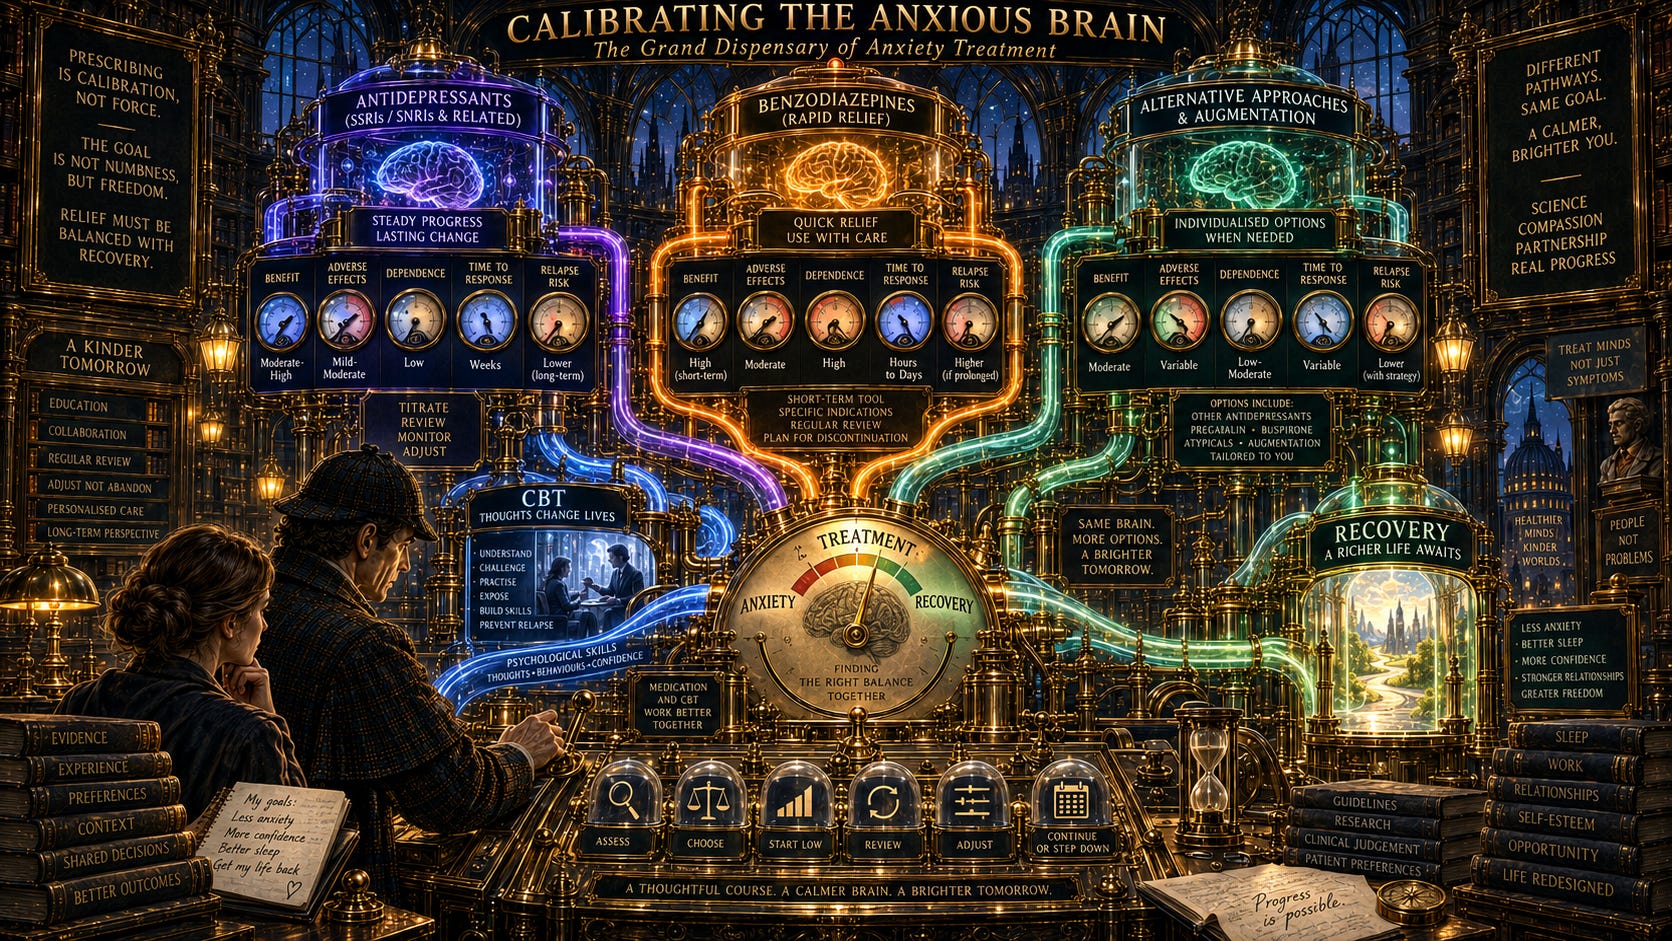
Medlock Holmes enters an immense Neo-Victorian treatment complex called The Grand Pharmacological Dispensary of Anxiety.Rows of treatment pathways stretch before him.Some contain SSRIs and SNRIs.Others hold benzodiazepines, pregabalin, buspirone, beta-blockers, older antidepressants, antipsychotics, neurostimulation devices, and emerging experimental therapies.But Holmes immediately notices that the first room contains no medication at all.It is labelled:ASSESS BEFORE YOU PRESCRIBE.Not every anxious person needs pharmacological treatment. Some symptoms are transient or subsyndromal. At the same time, clinically significant anxiety disorders remain frequently under-recognised and undertreated, particularly in primary care. Patients may describe insomnia, palpitations, gastrointestinal symptoms, pain or fatigue rather than saying, “I am anxious.” Screening tools such as the GAD-7 can improve recognition.Treatment therefore begins with diagnostic precision.What is the primary disorder?How severe is it?Are there medical causes?Substance use?Depression?Other anxiety disorders?Psychosocial stressors?Previous treatment response?Drug interactions?Patient preference?Cost and access?The treatment-choice diagram on page 3 captures this broader logic: illness factors, patient factors and medication factors all contribute to the decision.For many anxiety disorders, SSRIs and SNRIs are the first-line pharmacological treatments.Holmes watches clinicians begin low and increase gradually.Why?Because anxious patients can experience an early transient increase in nervousness, agitation or insomnia.The medications also require patience.Some improvement may appear within two to four weeks, but an adequate therapeutic trial generally requires 8–12 weeks, and remission may take considerably longer.The goal is not merely partial improvement.It is remission, because residual symptoms continue to impair functioning and increase relapse risk.Holmes then reaches the Benzodiazepine Chamber.Here the effect is strikingly different.The alarm quietens rapidly.Benzodiazepines enhance GABAergic inhibition and can reduce anxiety quickly.That makes them valuable in selected circumstances - short-term adjunctive treatment, occasional panic, performance-related anxiety, or severe disabling symptoms when alternatives have failed or are not tolerated.But the chamber contains warning plaques:Sedation.Dependence.Withdrawal.Tolerance.Interaction with alcohol.Driving impairment.Their speed is both their strength and their danger.Next comes pregabalin.It has evidence particularly in GAD and can be useful when insomnia or pain coexist.Buspirone occupies another chamber, particularly for chronic generalized anxiety.Beta-blockers sit in a small performance hall.They do not treat generalized social anxiety.Instead, they reduce peripheral manifestations such as tremor and tachycardia during specific performance situations.Older agents remain available but sit farther down the treatment hierarchy.TCAs can work but carry more anticholinergic effects, cardiotoxicity and overdose risk.MAOIs can be highly effective, particularly phenelzine in panic and social anxiety, but dietary restrictions, drug interactions and safety concerns make them second-line options.Holmes then passes through individual disorder galleries.In GAD, SSRIs and SNRIs dominate first-line treatment, with alternatives such as pregabalin, buspirone and selected other agents.In panic disorder, SSRIs and venlafaxine are preferred initial options, while benzodiazepines may provide rapid short-term relief.In social anxiety disorder, SSRIs and SNRIs again feature prominently; pregabalin and clonazepam have evidence, while beta-blockers are mainly relevant to performance anxiety.In specific phobia, however, the shelves are nearly empty.The principal treatment is psychological - especially exposure therapy. Pharmacotherapy has little established role and benzodiazepines may even interfere with exposure learning.This tells Holmes something important:The presence of anxiety does not automatically imply that medication is the best treatment.The next room is labelled:TREATMENT RESISTANCEBefore adding another medication, Holmes checks the foundations.Was the diagnosis correct?Was the dose adequate?Was the trial long enough?Is there thyroid disease?Substance use?Comorbid depression?Poor adherence?Drug interaction?Only then does he consider switching, augmentation, pregabalin, benzodiazepines, atypical antipsychotics or more experimental options.Beyond this room lies the Future Therapies Laboratory.rTMS.tDCS.Neurosteroids.Ketamine.Cannabinoids.Complementary therapies.Some show promise.But Holmes sees a large sign:PROMISING ≠ ESTABLISHEDThe evidence remains preliminary for many of these approaches.Finally, Holmes reaches the maintenance hall.The mistake here is stopping too soon.Anxiety disorders are frequently chronic or recurrent, and relapse after medication discontinuation is common.For many patients with chronic illness, medication may need to continue for 1–2 years after response, followed by gradual tapering rather than abrupt cessation.SSRIs and SNRIs can produce discontinuation symptoms, especially shorter-half-life agents such as paroxetine and venlafaxine.Holmes closes the final treatment ledger.The lesson is not that anxiety should simply be medicated.It is that somatic treatment should be deliberate, collaborative, evidence-based and disorder-specific.The right medication, for the right person, at the right dose, for the right duration, with careful monitoring - often alongside CBT - can transform disabling anxiety into something manageable.Key TakeawaysRecognition before treatment* Anxiety disorders carry substantial personal and societal burden.* Not every anxious symptom requires somatic treatment.* Transient and subsyndromal anxiety should not automatically be medicalised.* Nevertheless, clinically significant anxiety disorders are commonly under-recognised and undertreated.* Detection in primary care has historically been below 50%.* Only a minority of recognised cases receive appropriate evidence-based treatment.* Patients commonly present with physical rather than psychological symptoms.* Reluctance to disclose emotional symptoms can contribute to missed diagnosis.* Clinicians may fail to enquire directly about anxiety.* Detection improves as severity increases and with repeated healthcare attendance.* Structured screening tools such as the GAD-7 improve recognition.* Anxiety can often be effectively managed in primary care when properly identified.* Chronic physical illness and adverse social determinants increase vulnerability and should heighten clinical suspicion.Principles of Pharmacological ManagementThe chapter’s treatment principles can be summarised as:DIAGNOSE → ASSESS → EDUCATE → SELECT → MONITOR → OPTIMISEImportant elements include:* establish the primary diagnosis* identify psychiatric comorbidity* identify medical comorbidity* review current medications and substances* assess psychosocial stressors* document baseline severity and frequency* perform appropriate physical examination and laboratory investigation* discuss treatment options* incorporate patient preference* consider previous personal and family treatment response* check drug interactions* consider affordability and access* monitor progress using validated scales.The figure on page 3 groups treatment selection into three broad domains:Illness Factors* severity* frequency* chronicity* comorbidity* situational versus generalized symptoms.Patient Factors* preference* adherence* insight* psychological-mindedness.Medication Factors* previous response* family response* drug interactions* access* cost.Pharmacotherapy versus Psychotherapy* Initial evidence-based options include pharmacotherapy, CBT, or both.* Acute efficacy of medication and psychological therapy may be similar in many anxiety disorders.* Long-term comparative evidence is less complete.* Combination treatment is intuitively attractive but has not consistently been proven superior to either treatment alone.* Sequential addition of CBT after partial medication response is often a pragmatic strategy.* Patient preference should meaningfully influence treatment choice.SSRIs and SNRIsThese are the principal first-line pharmacological treatments across anxiety disorders.Common SSRIs include:* fluoxetine* sertraline* paroxetine* fluvoxamine* citalopram* escitalopram.Common SNRIs include:* venlafaxine* desvenlafaxine* duloxetine* levomilnacipran.Most guidelines favour an SSRI or venlafaxine as an initial antidepressant option.Start low, go slowAnxious patients can be particularly sensitive to early adverse effects.Initial treatment may temporarily increase:* nervousness* agitation* insomnia* tremor* gastrointestinal symptoms* headache* dizziness.Treatment is therefore usually started at a low dose and titrated gradually.Do not judge treatment too early* Early improvement may occur within 2–4 weeks.* A proper therapeutic trial generally requires 8–12 weeks at an adequate dose.* Some patients require substantially longer before remission.* The chapter notes that response or remission may sometimes take up to six months.Remission is the goalPartial response is not enough when substantial residual symptoms remain.Residual symptoms are associated with:* ongoing functional impairment* poorer quality of life* greater relapse risk.Treatment should therefore aim for:REMISSION + FUNCTIONAL RECOVERYrather than mere reduction in symptom score.SSRI/SNRI adverse effectsCommon effects include:* gastrointestinal disturbance* insomnia* nervousness* agitation* tremor* headache* dizziness* sexual dysfunction.Sexual dysfunction may involve:* reduced desire* impaired arousal* erectile dysfunction* delayed ejaculation* orgasmic dysfunction.The table on page 6 highlights meaningful differences between agents, with sexual adverse effects generally more frequent with several traditional SSRIs than with agents such as buspirone, mirtazapine or some newer antidepressants.Less common but clinically important SSRI/SNRI risksPotential serious complications include:* serotonin syndrome* seizures* induction of mania* hyponatraemia* gastrointestinal bleeding, particularly with NSAIDs* increased fracture risk in some older patients.These events are uncommon but clinically important.VenlafaxineVenlafaxine is among the most widely used SNRIs.Common adverse effects include:* dry mouth* sweating* constipation* insomnia* headache* sexual dysfunction.At higher doses, noradrenergic effects become more prominent.Dose-related hypertension occurs in a minority of patients, so blood pressure monitoring is appropriate at higher therapeutic doses.DuloxetineDuloxetine has broadly similar efficacy and tolerability to venlafaxine.Important considerations include:* discontinuation syndrome* gastrointestinal effects* avoidance or caution in significant hepatic dysfunction.Antidepressant discontinuation syndromeAbrupt cessation of SSRIs or SNRIs can produce:* anxiety* irritability* tearfulness* dizziness* light-headedness* malaise* sleep disturbance* concentration difficulty.Symptoms commonly emerge within 2–4 days.They are particularly associated with shorter-half-life medications such as:paroxetineandvenlafaxine.Gradual tapering is preferred.Fluoxetine’s long half-life can sometimes make it useful as a bridging strategy during difficult discontinuation.Antidepressants and suicidality* Regulatory warnings exist regarding treatment-emergent suicidal thoughts and behaviour in children and younger adults.* In adults aged 24 and above, short-term analyses reviewed in the chapter did not demonstrate a clear increased suicidality signal.* In younger patients, meta-analyses suggest an increase in suicidal thoughts and behaviours of roughly 1.5–2-fold, but not a corresponding increase in completed suicide.* The absolute increase in risk is small.* This must be balanced against the significant morbidity of untreated anxiety.* Medication can therefore remain appropriate in younger patients when clinically indicated, with careful monitoring.TCAsExamples include:* imipramine* clomipramine* amitriptyline* nortriptyline* desipramine* doxepin.TCAs inhibit monoamine reuptake but also affect:* muscarinic receptors* histamine receptors* α1 adrenergic receptors.This produces adverse effects such as:* dry mouth* constipation* blurred vision* sedation* weight gain* orthostatic hypotension.More serious issues include:* lowered seizure threshold* cardiotoxicity* toxicity in overdose.They are therefore usually second-line despite efficacy in some anxiety disorders.MAOIsCommon examples include:phenelzineandtranylcypromine.They can be highly effective, especially in:* social anxiety disorder* panic disorder.But their use is limited by:* dietary restrictions* tyramine-related hypertensive crisis* drug interactions* washout requirements* postural hypotension* weight gain* overdose concerns.They are generally reserved for refractory illness.RIMAsMoclobemide is the principal example discussed.Potential advantages over irreversible MAOIs include:* fewer dietary restrictions* generally better tolerability.It has evidence particularly in social anxiety disorder.Availability differs internationally.MirtazapinePotential advantages:* low propensity for sexual dysfunction* sedative properties can help insomnia* potential utility in panic and GAD.Limitations include:* increased appetite* weight gain* sedation* dry mouth* dizziness.Bupropion* Not generally a first-line treatment for primary anxiety disorders.* There is clinical concern that it may initially increase agitation or anxiety.* It is more often used to treat depression or as an adjunct to address antidepressant-associated sexual dysfunction.Vortioxetine* Multimodal serotonergic antidepressant.* Anxiety evidence has focused mainly on GAD.* Results remain preliminary or inconsistent.* Its use for anxiety is not as well established as SSRIs or SNRIs.AgomelatineActs via:* MT1/MT2 melatonin agonism* 5-HT2C antagonism.Potential advantages include:* low sexual dysfunction* little weight gain* minimal discontinuation syndrome.Evidence suggests possible benefit in GAD.Liver-function monitoring is recommended.VilazodoneCombines:SSRI activity + partial 5-HT1A agonismSome trials suggest benefit in GAD, but evidence remains insufficient to establish it alongside standard first-line treatments.BenzodiazepinesBenzodiazepines enhance GABAergic inhibition.They possess:* anxiolytic* sedative* anticonvulsant* muscle-relaxant properties.Common examples include:* clonazepam* lorazepam* alprazolam* diazepam* oxazepam* temazepam.Liver metabolismMost benzodiazepines undergo hepatic oxidative metabolism.Lorazepam, oxazepam and temazepam undergo conjugation and may therefore be preferable when hepatic function is impaired.A useful memory aid is:LOTLorazepamOxazepamTemazepamBenzodiazepine strengths* rapid onset* strong acute anxiolytic effect* predictable symptom relief* useful adjunct while antidepressants take effect* can be effective even in longer-term carefully selected use.Benzodiazepine limitationsImportant concerns include:* sedation* psychomotor impairment* driving risk* interaction with alcohol* dependence* withdrawal* misuse* potential tolerance.Avoid or use very cautiously in people with significant substance-use histories.Short-term adjunctive useBenzodiazepines may be prescribed for approximately 3–4 weeks when initiating an antidepressant to help manage:* severe anxiety* insomnia* jitteriness* delayed antidepressant onset.PRN benzodiazepinesMay be useful in selected situations such as:* occasional panic attacks* discrete performance anxiety.Frequent panic attacks are generally better treated preventively rather than repeatedly attempting to abort attacks with PRN benzodiazepines.PregabalinPregabalin has meaningful evidence in anxiety disorders, particularly GAD.Potential advantages include use where:* pain is comorbid* insomnia is prominent.Adverse effects include:* dizziness* drowsiness* weight gain.Pregabalin is primarily renally cleared, so renal impairment is an important consideration.Other anticonvulsantsAgents sometimes used include:* gabapentin* topiramate* tiagabine* lamotrigine* levetiracetam.Evidence is generally weaker or inconsistent compared with pregabalin.Atypical antipsychoticsAgents include:* quetiapine* olanzapine* risperidone* aripiprazole* ziprasidone* lurasidone.Evidence in primary anxiety disorders is limited.Quetiapine has demonstrated efficacy in GAD, but adverse effects limit its use.Key concerns include:* weight gain* metabolic syndrome* diabetes risk* lipid abnormalities.They are therefore generally later-line or augmentation strategies.Beta-blockersCommon options:* propranolol* atenolol.They reduce peripheral adrenergic symptoms such as:* tremor* tachycardia.Their principal role is performance anxiety.They are not effective treatments for generalized social anxiety disorder.Relevant contraindications include some:* cardiac disease* pulmonary disease* diabetes* angle-closure glaucoma.BuspironeBuspirone is an azapirone with serotonergic activity.It is primarily useful for:GADImportant characteristics:* not immediately acting* usually taken in divided doses* response develops over time* does not provide benzodiazepine-like rapid relief.HydroxyzineHydroxyzine is an antihistamine with evidence for GAD.Potential advantages:* relatively rapid early symptom relief* alternative to benzodiazepines in selected patients.Common adverse effects:* sedation* dry mouth* tremor.Tolerance to anxiolytic effects may develop.Treatment-resistant anxietyBefore labelling anxiety treatment-resistant:RECHECK THE CASESpecifically assess:* diagnosis* medical causes* thyroid disease* substance use* comorbid psychiatric disorders* adherence* drug interactions* adequate dose* adequate duration* access to effective CBT.Augmentation strategiesPossible augmentation agents include:* pregabalin* benzodiazepines* selected anticonvulsants* atypical antipsychotics.The evidence base is limited relative to first-line treatments.Treatment-resistant GAD is sometimes treated by adding pregabalin or a benzodiazepine to an SSRI/SNRI.For treatment-resistant panic disorder, clonazepam augmentation may be considered when CBT is unavailable or unsuitable.Novel TreatmentsrTMSEvidence for pure anxiety disorders remains limited.Some preliminary benefit has been reported for:* GAD* SAD* panic disorder.A small fMRI-guided GAD study reported promising results, but larger controlled trials are required.tDCSTranscranial direct-current stimulation is another non-invasive neuromodulation technique.Early reports suggest possible benefit in GAD and panic disorder, but evidence remains preliminary.NeurosteroidsIntranasal neurosteroidal compounds such as PH94B have shown promising results in social anxiety disorder.These remain investigational.KetamineKetamine has demonstrated substantial efficacy in treatment-resistant depression.Small studies suggest possible rapid anxiolytic effects in:* social anxiety disorder* GAD.The evidence remains insufficient to establish ketamine as standard treatment for primary anxiety disorders.CannabinoidsCannabinoids are increasingly used by patients seeking relief from anxiety.Some evidence suggests possible anxiolytic effects in GAD and SAD.However, the chapter emphasises major limitations:* heterogeneous preparations* inconsistent dosing* limited long-term data* methodological problems* publication bias.No firm therapeutic conclusions can therefore be drawn.Complementary and Alternative TherapiesPatients commonly use:* herbal preparations* acupuncture* yoga* biofeedback* supplements.Clinicians should actively ask about these treatments because herbal agents can cause clinically important drug interactions.KavaKava has some evidence for mild-to-moderate anxiety.However:* efficacy in specific anxiety disorders remains uncertain* hepatotoxicity is a concern* CYP-mediated drug interactions can occur.ExerciseAerobic exercise has evidence for reducing anxiety symptoms and provides substantial broader health benefits.The chapter supports routinely recommending physical exercise when appropriate.Yoga also has preliminary evidence, particularly in performance and other anxiety states.Duration of PharmacotherapyAn adequate acute trial generally requires:8–12 weeks at a therapeutic doseFor chronic anxiety disorders, continuing medication after response is usually necessary.Relapse studies report approximately:20–50% relapse within several months of antidepressant discontinuation.The chapter recommends maintenance therapy for many patients for approximately:1–2 yearsbefore considering discontinuation.TaperingDiscontinuation should be slow.The chapter describes dose reductions of roughly:10–25% every 1–2 monthswith monitoring for recurrence.Tapering must be individualised.Abrupt cessation should generally be avoided.Expected Pharmacotherapy ResponseApproximate response rates described in the chapter include:Panic disorder: 60–70%GAD: 50–60%Social anxiety disorder: 50–60%Panic disorder is therefore among the more pharmacologically responsive anxiety disorders.Agoraphobia may reduce response rates when comorbid with panic disorder.Evidence-Based Monotherapy PatternThe table on pages 17–18 provides a useful broad hierarchy.SSRIsFirst-line: SAD, GAD, PDSNRIsFirst-line: SAD, GAD, PDTCAs* not recommended in SAD* second-line in GAD* second-line in PDMAOIs* second-line in SAD* second-line in PD* limited evidence in GADBenzodiazepinesGenerally second-linePregabalin* strong role in SAD* second-line in GAD in the source’s summary table* insufficient evidence in PDQuetiapineSecond-line in GAD but limited by adverse effects.Generalized Anxiety DisorderPreferred pharmacological options include:SSRIsandSNRIsAlternatives include:* pregabalin* buspirone* quetiapine* mirtazapine* selected newer antidepressants.SSRIs are generally the preferred initial option.Pregabalin is another important option.Benzodiazepines are effective but usually restricted because of dependence and tolerance concerns.Quetiapine works but is generally second-line because of metabolic adverse effects.Propranolol has not demonstrated meaningful efficacy for GAD.Panic DisorderFirst-line pharmacological treatments include:SSRIsandvenlafaxineEffective older treatments include:* clomipramine* imipramine* phenelzine* tranylcypromine.Their adverse-effect burden places them later in the hierarchy.Benzodiazepines such as:* alprazolam* lorazepam* diazepam* clonazepamcan provide rapid short-term relief.Maintenance antidepressant treatment can prevent relapse for years in responsive patients.AgoraphobiaPharmacological evidence for pure agoraphobia is limited.Most pharmacological improvement occurs through treatment of:* panic disorder* depression* other comorbid anxiety disorders.CBT, especially exposure therapy, has a stronger direct evidence base.Social Anxiety DisorderFirst-line treatments described include:* SSRIs* SNRIs* pregabalin* clonazepam.Phenelzine is highly efficacious but generally second-line because of adverse effects and dietary restrictions.Other options include:* mirtazapine* moclobemide* selected benzodiazepines* gabapentin.Beta-blockers are useful for:PERFORMANCE ANXIETYbut not generalized social anxiety disorder.Specific PhobiaThis is the major exception to the medication-focused approach.Best-established treatment:EXPOSURE-BASED PSYCHOTHERAPYMedication evidence is very limited.SSRIs may occasionally be considered when psychotherapy fails or cannot be used.Benzodiazepines have not demonstrated clear benefit and may interfere with exposure-based learning.Therefore:SPECIFIC PHOBIA → THINK EXPOSURE FIRSTSeparation Anxiety DisorderEvidence is strongest in younger populations.SSRIs show benefit in studies of mixed paediatric anxiety populations including:* GAD* SAD* separation anxiety disorder.TCAs and clonazepam have not shown convincing benefit.Adult pharmacological data remain sparse.Selective MutismPsychosocial treatment is generally preferred.SSRIs such as:* fluoxetine* fluvoxaminemay be considered in more severe or treatment-resistant cases.Evidence remains considerably smaller than for other anxiety disorders.Children and AdolescentsAnxiety disorders are highly prevalent in young people.SSRIs and SNRIs have evidence in paediatric:* GAD* social anxiety disorder* separation anxiety disorder.Psychological treatment is often preferred initially, particularly for milder cases.Combination treatment may provide greater benefit in some paediatric anxiety disorders.Antidepressant treatment requires appropriate monitoring for treatment-emergent suicidal thoughts or behaviours.The chapter emphasises that the absolute risk is small and should be balanced against the morbidity of untreated anxiety.Optimising TreatmentThe chapter’s pharmacotherapy checklist can be condensed into:Aim for remission.Choose an evidence-based first-line drug.Start low.Increase gradually.Educate about adverse effects.Allow 8–12 weeks at an adequate dose.Use benzodiazepines selectively and usually short-term.Maintain successful treatment long enough to reduce relapse.Taper gradually.Add CBT when appropriate.The Central Clinical PrincipleSomatic treatment of anxiety is not:“The patient is anxious → prescribe an anxiolytic.”It is:Diagnosis → Severity → Comorbidity → Preference → Evidence → Safety → Adequate Trial → Monitoring → Remission → Maintenance → Careful DiscontinuationMedication should therefore be understood not as a universal antidote to anxiety, but as one component of a broader treatment strategy. This is a public episode. If you'd like to discuss this with other subscribers or get access to bonus episodes, visit drmanaankarray.substack.com/subscribe
Embed this episode
Ready to play
PSYCH 123: Anxiety Disorders - Somatic Therapies
No transcript for this episode yet
Similar Episodes
No similar episodes found.
Similar Podcasts
No similar podcasts found.